

OpenEvidence
Advertisements
App Specs
- Version
- 2.9.25
- Updated
- Nov 7, 2026
- Android Version
- 7.0
- Installs
- 500,000+
- Developer
- OpenEvidence
- Category
- Medical
- Content Rating
- Everyone
- Price
- Free
Screenshots



Our Review
 Analysis byUnlimiteds
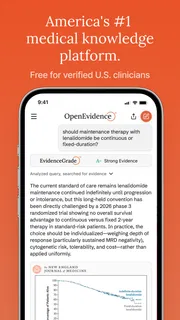
When a clinical question appears in the middle of a busy consultation, the difficult part is often not knowing that an answer exists somewhere. The difficult part is reaching useful evidence quickly, checking whether it applies to the patient in front of me, and turning it into a safe next step. That is the situation where OpenEvidence makes the most sense. It is a medical app from OpenEvidence designed to provide answers at the point of care, and its store summary makes clear that an NPI is required.
I approached it as a working tool rather than a general health search engine. That distinction matters. This is not the kind of app I would recommend to someone looking up ordinary symptoms at home, and it is not a replacement for a clinician, a patient record, or professional judgment. Its value is in helping a qualified user move from a focused clinical question toward an evidence-informed discussion without leaving the consultation completely.
The app is free and has an Everyone content rating, which makes the initial download feel approachable. It has also reached over half a million installs and holds a 4.9 average from roughly four and a half thousand ratings, so there is clear interest in this point-of-care approach. Still, those figures do not remove the need to understand the workflow. The NPI requirement immediately tells me that the intended audience is professional rather than casual.
From a patient question to a usable clinical answer
This section follows the path from a clinician’s initial uncertainty to an answer that can inform the next conversation or decision. I find it most useful to treat the search as a prompt for careful reasoning, not as a substitute for it. That distinction leads naturally to the practical question of how to shape the first query.
Starting with the right question
The quality of the experience begins before I type anything. A vague request such as “What should I do for this patient?” is too broad for any evidence tool to handle well. I get more value when I frame the question around a decision: whether a treatment is appropriate, what factors change the recommendation, how two options compare, or what evidence is relevant to a particular presentation.
That first step is one of the app’s less obvious lessons. OpenEvidence may make searching feel conversational, but a conversational interface does not make an imprecise question precise. I would include the clinical context that genuinely changes the decision while avoiding unnecessary identifying information. The goal is to describe the problem clearly enough for the answer to be useful, not to paste an entire chart into the search box.
For example, in a same-day consultation, I might first identify the patient’s main complaint, the key examination finding, the relevant history, and the decision I need to make. I would then ask a focused question about the evidence surrounding that decision. This creates a cleaner handoff from the patient encounter to the research step and makes it easier to judge whether the response actually addresses the problem.
Working through the response instead of stopping at the first sentence
Once the question is submitted, I treat the answer as a starting point for verification, not as an automatic instruction. The practical advantage of an evidence-focused app is that it can help organize a question around clinical reasoning. The practical risk is that a polished answer can feel more definitive than the underlying situation really is.
I would read the response with three checks in mind. First, does it answer the question I intended to ask? Second, does it distinguish general evidence from patient-specific judgment? Third, does it give me enough context to understand where the recommendation may not apply? Those checks are especially important when the patient has several conditions, unusual findings, or a treatment history that falls outside the typical scenario.
A useful workflow is to ask one broad orientation question, then follow it with narrower questions that test the important edges. I might ask what changes the recommendation, which patient groups require caution, or how competing approaches differ. This is more useful than repeatedly asking the same question in slightly different language, because it turns the app into a structured thinking aid rather than a one-line answer generator.
The strongest use is not replacing clinical reasoning, but shortening the distance between a focused question and the evidence I need to examine. That is a meaningful distinction for anyone deciding whether this belongs in a professional workflow.
Keeping the patient encounter moving
In a realistic consultation, there is rarely a clean block of research time. A patient may be waiting while I clarify a treatment choice, explain why a test is or is not useful, or prepare a handoff to another clinician. OpenEvidence fits best when I use it in short, deliberate passes: identify the uncertainty, search it, inspect the reasoning, and return to the patient conversation.
That approach also prevents a common mistake with medical search tools: collecting information without making a decision. I would write down the practical question before opening the app and, after reviewing the answer, state what has changed in my understanding. If nothing has changed, the search may have been too broad or the issue may require a deeper source.
The fact that the app is free removes a direct purchase barrier, but it does not remove the time cost of reading carefully. A free tool can still be inefficient if every response needs to be reinterpreted from scratch. I found that the best results come when I already know the decision point and use the app to support it, rather than expecting it to conduct the entire consultation for me.
Handoffs between clinician, evidence, and patient
The most important handoff is from the app back to the clinician. OpenEvidence can help surface relevant information, but I remain responsible for deciding whether it fits the patient’s circumstances. That means checking the answer against the history, examination, current treatment, contraindications, local practice, and any specialist input that may be needed.
The next handoff is from clinician to patient. I would not simply repeat technical wording from the screen. Instead, I would translate the useful part into plain language, explain the uncertainty, and discuss why a particular option is being considered. If the evidence points in more than one reasonable direction, that uncertainty is part of the conversation rather than something to hide.
There is also a handoff between clinicians. Suppose I use the app before speaking with a colleague or referring a patient. The helpful output is not “the app says this.” A better handoff includes the clinical question, the relevant patient factors, the evidence-based considerations I found, and the specific point on which I want another opinion. This keeps the tool in its proper role and makes the consultation more efficient.
Because an NPI is required, the onboarding itself is a meaningful part of the workflow. That requirement may reassure professional users that the app is designed for a clinical audience, but it also means it is not an instant public reference tool. Someone without the required professional identification should not assume that a free download will provide unrestricted access.
A realistic everyday scenario
Imagine I am preparing for a follow-up visit in which the patient’s symptoms have not improved as expected. The starting condition is uncertainty: I need to decide whether the next step should be continued observation, a change in management, additional evaluation, or discussion with another clinician. Rather than searching the entire symptom history, I would reduce the issue to a specific clinical question and enter only the context that affects that decision.
I would then review the answer for the main recommendation and the conditions that could change it. If the response raises a concern about a subgroup or a competing option, I would use that as the next question. Afterward, I would compare the information with the patient’s actual presentation and decide whether it supports the plan, changes the plan, or simply highlights the need for more expertise.
The final outcome is not a printed answer from the app. It is a better-prepared conversation: I can explain the options more clearly, identify why a particular next step is reasonable, and tell the patient when follow-up or escalation matters. If the answer does not resolve the uncertainty, that is still useful because it tells me not to force a confident conclusion from an incomplete picture.
What makes it different from ordinary alternatives
My usual alternatives in medical research are a general web search, a reference book, a guideline repository, a journal database, or a discussion with a colleague. Each has a place. A general search is quick but noisy. A textbook is useful for foundations but may be slower for a narrow point. A guideline can be authoritative and structured, though it may not answer the exact question I have in front of me. A journal database offers depth, but finding and interpreting the right material can take time.
OpenEvidence sits closer to the rapid question-and-answer end of that spectrum. Its appeal is the possibility of getting an organized response at the moment a decision needs clarification. That can be more convenient than opening several unrelated search results. The trade-off is that convenience can encourage premature closure. For a high-stakes or unusual case, I would still want to inspect primary literature, consult current guidance, or involve a specialist rather than treating a concise response as the final authority.
This is also why I would not compare it directly with a consumer symptom checker. A symptom checker starts with uncertainty about what a person might have. OpenEvidence is better understood as a professional evidence aid for a clinician who already has a clinical question. Using it as a self-diagnosis engine would be a mismatch between the tool and the user.
Practical strengths that are easy to overlook
One strength is the ability to use follow-up questions as a form of quality control. Instead of accepting the first response, I can probe the assumptions behind it. Asking about exceptions, patient factors, or alternative approaches turns the interaction into a small review process. This is particularly helpful when the initial question was written quickly during a busy clinic session.
A second strength is its usefulness before a handoff rather than only during a consultation. I can use a focused search to identify what needs to be clarified before contacting another clinician. That makes the eventual conversation more specific and avoids sending a vague request for help. The app does not replace the handoff; it can help me prepare for a better one.
A third insight is that the app works best as a decision-preparation layer. I would use it before explaining options to a patient, before discussing a case with a colleague, or before reviewing a management choice. I would be less comfortable using it as the only record of why a decision was made. The answer helps shape the discussion, while the clinical documentation and professional reasoning remain separate responsibilities.
Another useful habit is to keep the question and the conclusion distinct. I might search for evidence about an option, but the conclusion should include the patient-specific reasoning that led me to accept, reject, or postpone that option. This simple separation reduces the chance that a general answer will be mistaken for a personalized prescription.
Where the flow breaks
The first point of friction is access. Requiring an NPI makes sense for a professional medical product, but it limits who can use it and may slow down someone who expected a general-purpose health app. It also means that family members, students without the relevant identification, and patients looking for personal guidance should not choose it as their main resource.
The second limitation is the gap between an answer and an action. Even a relevant response cannot examine the patient, resolve missing history, assess urgency, or account for every local constraint. If the question is poorly framed, the response may be less helpful than a slower but more deliberate consultation of a guideline or specialist source.
There is also a risk of overconfidence. A clear response can create the impression that the clinical problem is settled when the real issue is uncertainty, conflicting evidence, or an atypical presentation. I would slow down whenever the answer affects a serious diagnosis, a vulnerable patient, a complex medication decision, or a situation where delay could cause harm.
Finally, the app should not become a substitute for learning the underlying subject. If I use it for every basic question, I may become dependent on retrieval instead of building durable knowledge. Its best role is selective: use it when a focused point needs checking, then return to broader references and professional education when the topic deserves deeper study.
Who should use it, and who should skip it
OpenEvidence is a strong fit for verified healthcare professionals who want a fast way to explore focused clinical questions during preparation, consultation, or handoff. It may also suit professionals who already know how to judge evidence and want a convenient first pass before opening more detailed sources. The free price makes experimentation easier, while the professional access requirement keeps the intended audience clear.
I would skip it if I were a patient seeking a diagnosis, a parent looking for immediate treatment instructions, or anyone wanting a simple explanation without clinical training. I would also choose a more traditional reference when I need exhaustive source review, detailed guideline navigation, or a deep examination of conflicting studies. In those situations, speed is less important than completeness and traceability.
My final view after following the workflow
OpenEvidence is most convincing when I follow the complete path: start with a real clinical uncertainty, phrase it narrowly, examine the response critically, test its limits with follow-up questions, and then carry the useful information into a patient or colleague conversation. That workflow gives the app a practical purpose beyond simply producing text.
It is not a magic shortcut, and the NPI requirement makes clear that it is not aimed at everyone. The answer still needs professional interpretation, and difficult cases still deserve established references and human expertise. But for the right user, it can reduce the friction between a point-of-care question and a more informed next step.
OpenEvidence was released on October 1, 2024, and the current version is 2.9.25, with support beginning at Android 7.0. Those details make it accessible across a broad range of Android devices, while the app’s medical focus defines how it should be used. My recommendation is straightforward: if you are a qualified clinician who wants a fast evidence-oriented starting point, it is worth trying. If you need personal health advice or a complete research archive, choose a resource built for that purpose instead.
Pros and Cons
Pros
- Quick access to evidence-based medical information for clinical questions.
- Citations and source links make claims easier to verify.
- Designed for healthcare professionals rather than general audiences.
- AI-assisted answers can help summarize complex medical literature.
- Useful on mobile when a rapid point-of-care reference is needed.
Cons
- Medical content may require independent verification before guiding patient care.
- Access and features can depend on professional eligibility or account approval.
- AI responses may occasionally lack context or misinterpret a question.
- Coverage and answer quality can vary by specialty and topic.
- Not a replacement for clinical judgment
- guidelines
- or local protocols.
Advertisements
How It Compares
| App | Rating | Installs | Price |
|---|---|---|---|
 OpenEvidenceOpenEvidence | 4.9 | 500,000+ | Free |
 WebMD: Symptom CheckerWebMD, LLC | 4.1 | 10,000,000+ | Free |
 CVS HealthCVS Pharmacy | 4.5 | 10,000,000+ | Free |
 MyChartEpic Systems Corporation | 4.4 | 10,000,000+ | Free |
Alternatives Worth Trying


More Medical Reviews
View All More Medical Reviews


Frequently Asked Questions
What is OpenEvidence and who is it designed for?
OpenEvidence is an AI-powered medical information platform designed primarily for healthcare professionals, including physicians, nurses, and other clinical users. It is intended to help users find concise, evidence-based answers to medical questions and review supporting sources more efficiently. It should be treated as a clinical reference and decision-support tool, not as a replacement for professional judgment, institutional protocols, or direct patient evaluation.
Can OpenEvidence be used to diagnose patients or replace a doctor’s advice?
No. OpenEvidence should not be used as an autonomous diagnostic system or as a substitute for a qualified healthcare professional. Its responses may help clinicians explore medical evidence, but AI-generated information can be incomplete, outdated, or misinterpreted. Users should verify important details against current guidelines, original research, patient records, and local policies before making treatment or diagnostic decisions.
Does OpenEvidence provide sources for its medical answers?
OpenEvidence is designed to present medical information together with supporting evidence or references, which can make it easier to investigate a topic further. However, users should still review the cited material carefully because the relevance and quality of sources may vary depending on the question. For high-risk clinical decisions, checking the original publication and the latest official guidelines remains essential.
Is OpenEvidence free to download and use?
Access to OpenEvidence may depend on the platform, region, account type, and eligibility requirements. Some users may be able to register without charge, while certain features or professional access could require verification, an invitation, or an associated healthcare organization. Before downloading, review the current listing and the app’s terms so you understand any limitations, subscriptions, or access conditions that apply.
Is patient information safe to enter into OpenEvidence?
Users should be extremely careful when entering clinical information into any AI application. Avoid submitting names, contact details, medical record numbers, photographs, or other identifiable patient data unless the service is explicitly approved for that use by your organization and complies with applicable privacy requirements. Use de-identified information whenever possible, and review OpenEvidence’s privacy policy before using it in clinical workflows.
Advertisements

Download OpenEvidence
About This Listing
- Last Checked
- Nov 7, 2026
- Version Reviewed
- 2.9.25
- Source
- Official Stores
This listing provides independent information about Unlimiteds. We do not own, develop, or distribute this app. All names, logos, and trademarks belong to their respective owners. Developer details are provided for reference; please contact the developer through the links listed on this page.